

A physician-supervised medical weight loss clinic treats obesity as a chronic disease under a doctor’s direct care, and choosing the wrong clinic exposes patients to undertreated chronic disease, wasted money, and safety risks. Atlanta’s medical weight loss market spans board-certified obesity medicine physicians and minimally supervised dispensaries operating behind a thin medical veneer. Eight concrete verification criteria, from physician credentials to pricing transparency, give patients an evidence-grounded framework for evaluating any medical weight loss clinic before committing a dollar.
What Does ‘Physician-Supervised Medical Weight Loss’ Actually Mean, and Why Does the Definition Matter When Choosing a Clinic?
Physician-supervised medical weight loss means a licensed physician personally evaluates each patient, orders and interprets laboratory testing, designs the treatment plan, and directs follow-up care. The definition matters because ‘medical weight loss’ is an unregulated term that any clinic can use, regardless of physician involvement.

No Georgia licensing category or federal rule controls the phrase, so a med spa, a chiropractic office, and an internal medicine practice can advertise under the identical label. That produces two very different products behind one marketing term. Nominal supervision places a physician’s name on the paperwork while non-physician staff run intake, prescribe, and manage patients. Active clinical oversight puts the physician inside the care loop at three specific points.
Active physician supervision requires the physician at each stage of care:
- At intake: the physician takes a full medical history, reviews comorbidities such as hypertension, type 2 diabetes, and sleep apnea, and orders baseline laboratory testing before recommending any therapy.
- During treatment: the physician designs and signs the treatment plan, interprets lab results, and manages prescriptions such as GLP-1 weight-loss therapy directly. A physician assistant or health coach never builds the plan independently.
- At follow-up: the physician reviews progress, side effects, and repeat labs at scheduled intervals and adjusts the plan personally.
Patients who know what to expect from supervised programs can spot a missing step during a single consultation.
The stakes are local. According to Healthbeat’s 2025 analysis of CDC Behavioral Risk Factor Surveillance System data, Georgia’s adult obesity rate reached 35.4% in 2024, ranking No. 19 in the nation. The CDC’s 2024 data also places Georgia among the 23 states with adult obesity rates of 35% or higher, and demand at that level sustains a crowded Atlanta market where clinics apply the medical label loosely.
Some Atlanta clinics market aggressively under the medical label while operating primarily as aesthetics or spa businesses that added weight loss as a revenue stream. The absence of a full-time, on-site physician is a quick disqualifier, and the staffing test described in clinical vs commercial weight loss compared gives patients a fast first screen.
Definitional clarity comes first because every other verification criterion depends on it. Credentials, lab protocols, follow-up schedules, and pricing only become verifiable once a patient can separate real oversight from a borrowed name on the door. The good news for patients is that once the physician question is settled, the remaining seven criteria become quick, confident checks rather than guesswork.
What credentials should the physician at a medical weight loss clinic have?
The supervising physician should hold board certification in obesity medicine (ABOM), the gold standard, or a primary board certification in internal medicine, endocrinology, or family medicine paired with dedicated obesity training. Every credential should be verifiable by you before enrollment.

Board certification in obesity medicine (ABOM) is a verifiable credential patients should confirm before enrolling. ABOM designates physicians who complete its certification process as Diplomates, and according to the American Board of Obesity Medicine (2023), certification formally distinguishes physicians as having achieved competency specifically in obesity care. Any licensed physician can legally prescribe GLP-1 medications, but only ABOM-certified physicians have completed dedicated training in obesity as a chronic disease. Look the physician up on the ABOM public directory rather than taking a clinic’s word for it. ABOM reported in 2025 that more than 11,500 physicians held certification in the United States and Canada as of October 2025, so qualified candidates are easier to find than many patients assume.
Adjacent credentials also provide a sound foundation. A 2025 PubMed analysis found the most common primary specialties among ABOM diplomates are internal medicine (32.4%) and family medicine (29.2%), and endocrinology adds strong metabolic training. Physicians holding Fellowship of Obesity Medicine Society (FOMA) membership or completion of an obesity medicine fellowship program offer additional positive signals even while ABOM certification is still pending.
A clinic led by a nurse practitioner or physician assistant with only nominal physician oversight does not meet the physician-supervised standard. Georgia’s verification portal lists approved supervisors for physician assistants, which reveals whether the named physician actively supervises or simply lends a name to the door.
Verify credentials before your first appointment, not after. The Georgia Composite Medical Board’s online portal confirms any physician’s active license and displays public board orders. The credentials a weight loss doctor should have appear in both the ABOM directory and the state portal, and a legitimate clinic will always welcome that check.
What should a medical weight loss clinic do at your first appointment, and what does it mean if they skip these steps?
A legitimate physician-supervised program requires baseline laboratory work and a comprehensive medical intake before any treatment begins. A first appointment should produce blood results, a documented health history, body composition data, and a physician’s evaluation before any prescription is written.
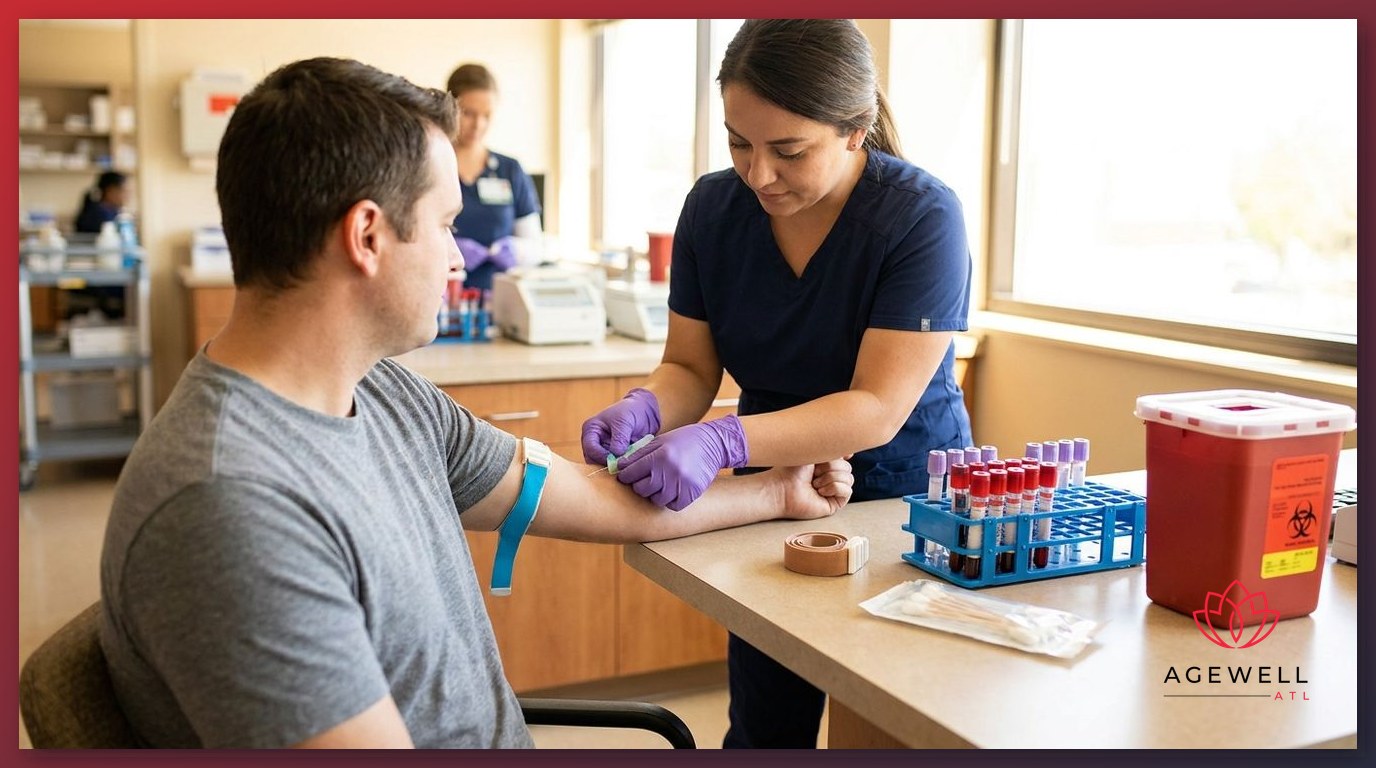
A thorough first visit takes time, and that time protects the patient:
1. Baseline laboratory work. The clinic orders a comprehensive metabolic panel, thyroid function tests, HbA1c, and a lipid panel before prescribing anything. According to Personalabs.com (2024), prescribers typically request lab work completed within the past six months before initiating GLP-1 therapy, because a comprehensive metabolic workup screens for contraindications. 2. Comprehensive medical history review. The physician documents comorbidities, a complete medication list, prior weight loss attempts, and potential contraindications. The medical history review at intake shows which findings change a treatment plan. 3. Body composition assessment. Scale weight and BMI alone are insufficient clinical data. A medical weight loss clinic measures body fat percentage, lean mass, or waist circumference so progress tracks fat loss rather than scale weight.
The key intake questions for clinics cover these same three steps, so patients can ask about each one directly.
Skipping labs is the single fastest differentiator between a clinical program and a dispensary model. Personalabs.com (2024) reports that GLP-1 medications interact with the pancreas, kidneys, thyroid, and liver, and without a pre-treatment baseline, medication-related lab changes cannot be distinguished from pre-existing ones. A clinic that prescribes GLP-1 receptor agonists without baseline thyroid, metabolic, and HbA1c testing cannot safely rule out contraindications; that prescription is driven by commerce, not medicine.
Some clinics also outsource laboratory work and add significant markups. Patients are entitled to ask which lab a clinic uses and whether baseline bloodwork can be completed at their own insured lab.
How do you know if a clinic’s treatment plan is truly individualized — or just a one-size-fits-all protocol?
An individualized plan is built from your labs, comorbidities, lifestyle, and medical history, and the plan changes when your response does. A cookie-cutter clinic prescribes the same treatment to every patient and has no answer when the first approach fails.

1. Ask what drives treatment selection. In a genuinely individualized program, the physician selects treatment based on your lab results, comorbidities, lifestyle factors, and patient history. A single default offering handed to every new patient signals the opposite. 2. Count how many tools the clinic uses. An individualized treatment protocol is distinguished from a cookie-cutter single-drug program applied identically to every patient by the range of options behind the plan. When every patient leaves with the same GLP-1 receptor agonist prescription, the clinic is matching patients to a product rather than matching a tool to the patient. 3. Ask two revealing questions. “What happens if the first treatment doesn’t work?” and “Do all your patients receive the same protocol?” expose whether a real fallback plan exists. The medically supervised options for treatment-resistant weight gain describe the alternatives a physician should have ready, so listen for specifics rather than vague reassurance. Any clinic worth your trust will welcome both questions. 4. Check what surrounds the medication. GLP-1 medications are an important tool in obesity medicine, and GLP-1 therapy delivers its best results inside a program that includes behavioral and nutritional support. A clinic offering GLP-1 medications with no behavioral, nutritional, or lifestyle component is providing prescriptions, not comprehensive obesity medicine, and that distinction matters for long-term outcomes.
What ongoing monitoring should a legitimate medical weight loss program provide after treatment begins?
Ongoing monitoring includes scheduled follow-up visits, metabolic labs, and body composition tracking, not just prescription refills. A physician reviews your response, adjusts your treatment, and catches adverse effects early throughout your care.

During the first 90 days, a responsible schedule brings you back to the physician every few weeks while dosing is established, then spaces visits out once your response stabilizes. The question that separates genuine oversight from a refill-mill is “how often will I see or speak with the physician (not a medical assistant or patient coordinator) after starting treatment?” Ethical programs answer with a structured schedule, not “as needed.”
Repeat laboratory work at defined intervals tracks your metabolic response and flags adverse effects before they become problems. Progress measurement should reach beyond scale weight to body composition, blood pressure, HbA1c trajectory, and patient-reported outcomes such as sleep, energy, and hunger.
Automatic refills with no physician contact, touchpoints handled only by a patient coordinator, and the absence of any defined follow-up schedule all signal a refill-mill model. Strong programs also plan for what happens if medication ends, because according to a 2026 Medscape report, cardiometabolic improvements from GLP-1 therapy return to baseline within roughly 1.4 years after discontinuation.
If earlier programs have failed you, ask how the clinic handles weight loss plateaus. The answer reveals whether the team adapts your protocol or simply repeats it, and it belongs on your personal list of what to ask your injection provider before you enroll.
How should a legitimate medical weight loss clinic present its pricing, and what are the cost-related red flags?
A legitimate medical weight loss clinic publishes itemized pricing for intake, labs, physician visits, treatments, and follow-up care before enrollment. Transparent pricing disclosure is a mandatory quality signal, and any clinic that hides costs until after a consultation raises an immediate red flag.

1. Request a written, itemized quote before enrolling. The quote should list the initial consultation, laboratory panels, physician follow-up visits, and each treatment component, including GLP-1 medications or peptide therapy when prescribed. Comparing that quote against typical fees at medical weight loss clinics helps you spot outliers before you commit.
2. Recognize the classic pricing red flags. Be cautious with all-inclusive bundles that never explain what is inside, large upfront program fees with no itemization, and quotes that surface only after the staff has built rapport with you. Honest clinics put numbers on paper early.
3. Compare value rather than sticker price. The cheapest clinic is rarely the safest or most effective choice. When two quotes differ significantly, compare physician involvement, lab monitoring frequency, follow-up access, and staff credentials instead of the monthly total alone.
4. Verify insurance directly with the clinic and your insurer. Most Atlanta clinics operate on a self-pay basis, Georgia Medicaid excludes weight-loss medications for most adults, and many Georgia employer plans require prior authorization or exclude anti-obesity treatment entirely. Confirm your specific benefits with the clinic’s billing staff, because Georgia insurance coverage for weight loss varies widely by plan.
Is a telehealth-only weight loss clinic a safe alternative to an in-person physician-supervised program?
A telehealth-only clinic can safely handle routine follow-up for stable patients, but it cannot match the oversight of an in-person physician-supervised program, especially for patients starting GLP-1 medications or managing conditions like hypertension and type 2 diabetes.

Telehealth-only programs deliver genuine convenience: virtual visits, flexible scheduling, and prescriptions managed from home. That convenience has hard limits. A remote provider cannot perform a physical examination, run in-office body composition testing, or complete a hands-on clinical assessment such as heart and lung auscultation.
Those limits carry the most weight for patients with comorbidities. Hypertension, type 2 diabetes, and cardiovascular risk all require physical monitoring, including measured blood pressure, weight trends, and periodic labs interpreted alongside an exam, so a telehealth-only model cannot replace an in-person physician-supervised program for these patients.
The structural gap is oversight depth. Telehealth-only prescribers differ from in-person physician-supervised clinics in the depth of clinical oversight they can provide. Some telehealth-only GLP-1 prescribing models run on a brief intake form with minimal physician involvement, so patients weighing telehealth versus in-person weight loss care should ask concrete questions: Who reviews my history and labs? Is a licensed physician reachable when side effects appear? How often will someone re-examine me?
Telehealth follow-up is a legitimate complement to in-person care, not a substitute for it. Once a physician completes the initial physical evaluation and baseline labs, virtual check-ins for progress reviews, medication adjustments, and nutrition coaching work well. Sequence is the distinction: remote visits extend a program that begins with an examination.
What are the clearest red flags that a weight loss clinic is operating below the standard of care?
The clearest red flags are guaranteed outcome claims, missing lab work at intake, high-pressure sales tactics, refusal to name the supervising physician, and identical cookie-cutter protocols for every patient. Each pattern signals a dispensary model rather than physician-supervised medical care. The warning signs at weight loss clinics explains how each of these patterns violates a specific standard of clinical care.
- Guaranteed weight loss claims. A claim such as “lose 30 pounds in 30 days” is a red flag and a potential regulatory violation. No ethical clinic promises specific outcomes, because results vary with each patient’s biology, adherence, and starting health.
- Missing lab work. A clinic that skips lab testing at intake or during treatment displays the single clearest marker of a dispensary model masquerading as a clinical program. Physicians cannot safely prescribe or adjust treatment without baseline metabolic data.
- High-pressure sales tactics. Large non-refundable upfront payments and pressure to enroll the same day place revenue ahead of patient care. A reputable program provides written pricing and gives you time to decide.
- Undisclosed physician. A clinic that cannot or will not share the supervising physician’s name, credentials, or role in your specific care is withholding the exact information you need to verify real oversight.
- Cookie-cutter protocols. A program that hands every patient the identical plan regardless of medical history, current medications, or lab results abandons the individualization that safe medical weight loss requires.
